Depemokimab Improves Quality of Life in Uncontrolled Type 2 Asthma, With Benefits Sustained Through 52 Weeks
1-minute summary
Twice-yearly depemokimab was associated with early and sustained improvements in asthma-related symptoms, physical activity, daily-life impact, and quality of life among patients with uncontrolled type 2 asthma. Findings from an analysis of the phase 3 SWIFT-1 and SWIFT-2 studies were presented at the CHEST Annual Meeting, held October 18–21, 2026, in Phoenix, Arizona.
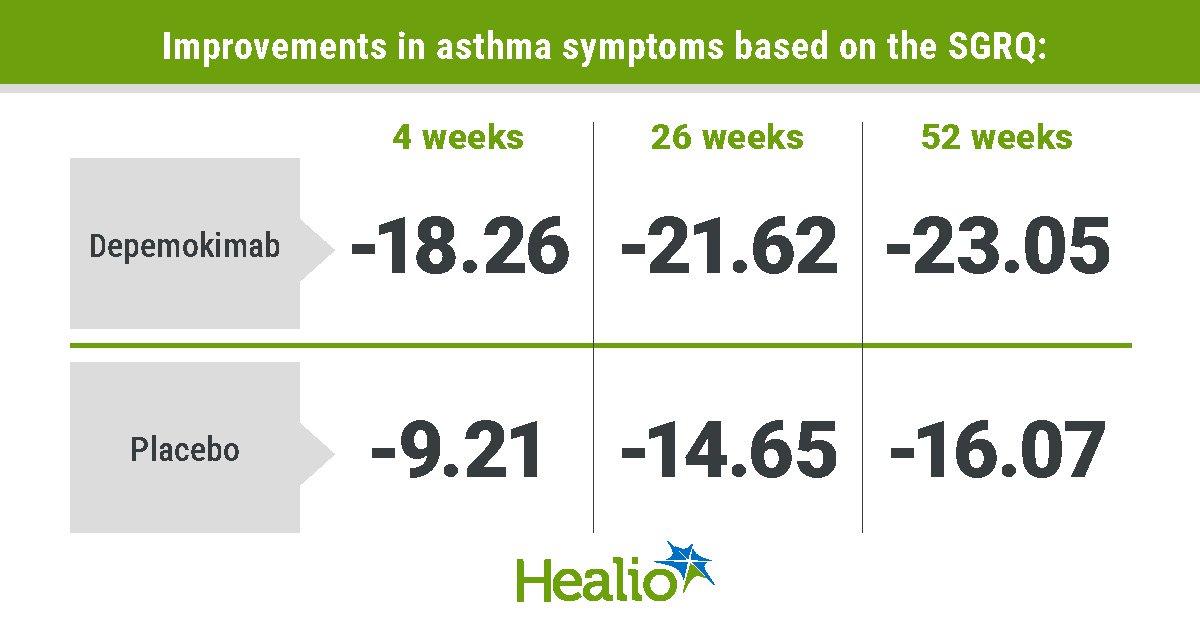
The analysis included 559 patients with a baseline Asthma Control Questionnaire-5 (ACQ-5) score of at least 1.5. Of these, 363 received subcutaneous depemokimab 100 mg every 26 weeks, while 196 received placebo. Improvements in St. George’s Respiratory Questionnaire (SGRQ) scores were apparent as early as week 4 and persisted through weeks 26 and 52.
At week 52, the mean change in the SGRQ symptoms-domain score was −23.05 with depemokimab compared with −16.07 with placebo. Improvements were also observed in the activity and impacts domains.
The investigators concluded that twice-yearly dosing may reduce treatment burden while providing sustained improvements in patients’ reported health status. However, the findings were presented as conference-poster data, and the supplied report does not provide a full publication, confidence intervals, or statistical significance estimates for these quality-of-life outcomes.
Why this matters
Uncontrolled asthma can affect more than respiratory symptoms. It may limit physical activity, disrupt everyday tasks, and reduce patients’ overall well-being. Biologic treatments can improve disease control, but the frequency and practical demands of treatment may also influence long-term adherence.
Depemokimab is administered subcutaneously every 26 weeks, offering a twice-yearly dosing schedule. If supported by the broader clinical evidence and appropriate for an individual patient, this extended interval could reduce the frequency of treatment administration.
The reported improvements across symptoms, activity, and daily-life impact suggest that the potential benefits may extend beyond symptom control alone. Nevertheless, these results should be interpreted as patient-reported quality-of-life findings; they do not, by themselves, establish effects on exacerbations, lung function, hospitalization, or corticosteroid use.
Study at a glance
| Feature | Details |
|---|---|
| Study type | Quality-of-life analysis of two phase 3 clinical trials |
| Trials | SWIFT-1 and SWIFT-2 |
| Participants | 559 patients with uncontrolled type 2 asthma and baseline ACQ-5 score ≥1.5 |
| Intervention | Subcutaneous depemokimab 100 mg every 26 weeks |
| Comparator | Placebo |
| Treatment group | 363 patients |
| Placebo group | 196 patients |
| Assessment period | Baseline through 52 weeks |
| Main outcome assessed | Changes in SGRQ symptoms, activity, and impacts-domain scores |
| Main finding | Improvements were observed by week 4 and persisted through weeks 26 and 52 |
| Presentation | CHEST Annual Meeting, October 18–21, 2026 |
| Original research DOI | Not provided in the supplied report |
What the researchers found
The analysis evaluated changes in three domains of the St. George’s Respiratory Questionnaire: symptoms, activity, and impacts. SGRQ scores measure respiratory health status, with lower scores generally indicating fewer problems and better health-related quality of life.
Across all three domains, mean scores decreased in both groups. The reported reductions were consistently greater in the depemokimab group at weeks 4, 26, and 52.
1. Symptoms domain
The depemokimab group demonstrated a greater mean reduction in SGRQ symptoms scores than the placebo group at each reported assessment.
| Assessment | Depemokimab: mean change (n) | Placebo: mean change (n) | Between-group difference in mean change* |
|---|---|---|---|
| Week 4 | −18.26 (346) | −9.21 (189) | −9.05 |
| Week 26 | −21.62 (342) | −14.65 (190) | −6.97 |
| Week 52 | −23.05 (332) | −16.07 (178) | −6.98 |
*Calculated by subtracting the placebo mean change from the depemokimab mean change. These are descriptive differences, not reported adjusted treatment effects.
The largest reduction in the depemokimab group was observed at week 52, when the mean change from baseline reached −23.05, compared with −16.07 in the placebo group.
2. Activity domain
The activity domain assesses the extent to which respiratory problems affect physical activities.
| Assessment | Depemokimab: mean change (n) | Placebo: mean change (n) | Between-group difference in mean change* |
|---|---|---|---|
| Week 4 | −12.33 (346) | −7.69 (189) | −4.64 |
| Week 26 | −15.66 (342) | −10.40 (190) | −5.26 |
| Week 52 | −17.82 (332) | −13.24 (178) | −4.58 |
*Descriptive differences calculated from the reported mean changes.
Improvements in activity scores persisted through 52 weeks. At the final reported assessment, the mean change was −17.82 with depemokimab and −13.24 with placebo.
3. Impacts domain
The impacts domain evaluates the broader effects of respiratory disease on everyday life.
| Assessment | Depemokimab: mean change (n) | Placebo: mean change (n) | Between-group difference in mean change* |
|---|---|---|---|
| Week 4 | −11.95 (346) | −6.98 (189) | −4.97 |
| Week 26 | −13.54 (342) | −8.19 (190) | −5.35 |
| Week 52 | −15.56 (332) | −9.77 (178) | −5.79 |
*Descriptive differences calculated from the reported mean changes.
The impacts-domain scores also improved over time, with a greater reduction in the depemokimab group at each assessment. By week 52, the between-group difference in mean change was −5.79 points.
4. Overall pattern of improvement
| Domain | Week 4: difference* | Week 26: difference* | Week 52: difference* |
|---|---|---|---|
| Symptoms | −9.05 | −6.97 | −6.98 |
| Activity | −4.64 | −5.26 | −4.58 |
| Impacts | −4.97 | −5.35 | −5.79 |
*Descriptive differences in mean change, depemokimab minus placebo; more negative values favor depemokimab because lower SGRQ scores indicate improvement.
These results show a consistent numerical advantage for depemokimab across all three domains at every reported time point. The supplied report does not include confidence intervals or P values for these comparisons, so the magnitude and statistical precision of the treatment differences cannot be fully assessed from this information alone.
Clinical significance
The findings suggest that depemokimab may improve several dimensions of health-related quality of life in patients with uncontrolled type 2 asthma.
Early response: Improvements were apparent by week 4, suggesting that changes in patient-reported respiratory health status may emerge relatively early during treatment.
Sustained benefit: Reductions in SGRQ scores continued through weeks 26 and 52, supporting the possibility that improvements can persist during a twice-yearly dosing regimen.
Potential reduction in treatment burden: Administration every 26 weeks may be more convenient than treatments requiring more frequent injections. Whether this translates into better adherence, fewer missed doses, or improved long-term outcomes was not established by the reported quality-of-life analysis.
Patient-centered outcomes: Assessing symptoms, activity limitations, and everyday impacts complements conventional measures of asthma control. These domains can help clinicians understand how patients experience their disease and treatment.
The results should not be interpreted as proof that depemokimab is superior to other biologics, that every patient will experience clinically meaningful improvement, or that the drug reduces asthma exacerbations on the basis of this analysis alone.
Limitations
Several limitations should be considered when interpreting these findings:
- Conference-poster data: The results were presented at the CHEST Annual Meeting. The supplied report does not provide a complete peer-reviewed publication of this analysis.
- Incomplete statistical reporting: Confidence intervals, P values, and adjusted between-group treatment estimates were not included in the supplied material.
- Selected study population: The analysis included patients with a baseline ACQ-5 score of at least 1.5. The findings may not apply equally to all patients with asthma, particularly those with better baseline control or different disease characteristics.
- Patient-reported measures: SGRQ outcomes provide important information about perceived health status but do not independently establish changes in lung function, exacerbation rates, hospitalizations, or other clinical endpoints.
- Follow-up duration: The reported analysis covered 52 weeks. It does not establish whether the observed improvements persist over longer periods.
- No head-to-head comparison: The findings do not establish comparative effectiveness against other biologic therapies.
- Potential for attrition: The numbers contributing data decreased between the baseline analysis population and the later assessments. The supplied report does not provide enough information to determine how missing data were handled or whether attrition affected the estimates.
What doctors should know
- Identify the relevant population: The reported results concern patients with uncontrolled type 2 asthma who had an ACQ-5 score of at least 1.5 at baseline.
- Recognize the dosing interval: The study regimen used subcutaneous depemokimab 100 mg every 26 weeks.
- Discuss patient-reported benefits: Improvements were reported in symptoms, activity, and the effects of asthma on everyday life, with numerical differences favoring depemokimab at weeks 4, 26, and 52.
- Avoid overinterpreting conference results: The supplied report does not provide the statistical details needed to independently assess the precision or significance of each treatment difference.
- Use a comprehensive assessment: SGRQ changes should be considered alongside asthma control, exacerbation history, lung function, treatment history, comorbidities, patient preferences, and relevant prescribing information.
- Do not assume universal suitability: The results do not establish that depemokimab is appropriate for every patient with uncontrolled asthma or that it should replace another biologic without an individualized clinical assessment.
Bottom line
In a quality-of-life analysis of 559 patients from the phase 3 SWIFT-1 and SWIFT-2 studies, twice-yearly subcutaneous depemokimab was associated with greater mean improvements in SGRQ symptoms, activity, and impacts scores than placebo. Improvements were evident at week 4 and persisted through week 52. The extended dosing interval may reduce treatment burden, but the clinical interpretation of these findings requires the full statistical analysis and consideration of the broader efficacy and safety evidence.
Original research / DOI
Conference presentation: Pavord ID, et al. Twice-yearly depemokimab is associated with early and sustained improvements in quality-of-life domains in patients with uncontrolled type 2 asthma in SWIFT-1/-2.
Presented at: CHEST Annual Meeting, October 18–21, 2026; Phoenix, Arizona.
DOI: Not provided in the supplied report.
Disclosure: Ian D. Pavord reported financial relationships with AstraZeneca, Boehringer Ingelheim, Chiesi, Circassia, Genentech, GSK, Knopp, Merck, Novartis, Regeneron, Sanofi, and Teva.