Evaluation of Gabapentinoid Use and Fracture Risk in Older Adults: Findings From a Multinational Cohort Study
Importance
The prescribing of gabapentinoids (gabapentin and pregabalin) in older adults is common, yet concerns regarding their association with adverse events, including falls and subsequent fractures, remain prevalent. Recent findings from a population-based, multinational retrospective study published in The Lancet Healthy Longevity suggest that while an acute risk exists, long-term gabapentinoid treatment may not be independently associated with a sustained increase in fracture risk for older adult populations.
Objective and Design
Led by Kenneth K. C. Man, PhD, CStat, FHEA, FRSM, FRSPH, a pharmacoepidemiologist and medical statistician at University College London, alongside Andrew S. C. Yuen, PhD, and colleagues, the researchers sought to quantify fracture risk across different periods of gabapentinoid treatment.
The retrospective study evaluated adults aged 60 years or older who had been prescribed either pregabalin or gabapentin and subsequently required hospitalization for a fracture. The investigation pooled patient data from two large-scale national databases: the United Kingdom’s Clinical Practice Research Datalink (CPRD) and the South Korean National Health Insurance Service-National Health Screening Cohort.
| Patient Demographics and Data Sources | United Kingdom Cohort | South Korean Cohort |
| Study Period | 2010 – 2020 | 2003 – 2019 |
| Total Participants ($N$) | 20,030 | 2,935 |
| Mean Age (Years) | 77.85 | 69.24 |
| Sex (Proportion of Women) | 76.7% | 68.4% |
Methodology and Key Findings
To accurately track fluctuating risk levels, the investigators stratified the patients’ observation periods into four distinct chronological windows related to their gabapentinoid prescriptions. The analysis utilized a random-effects model to pool the results.
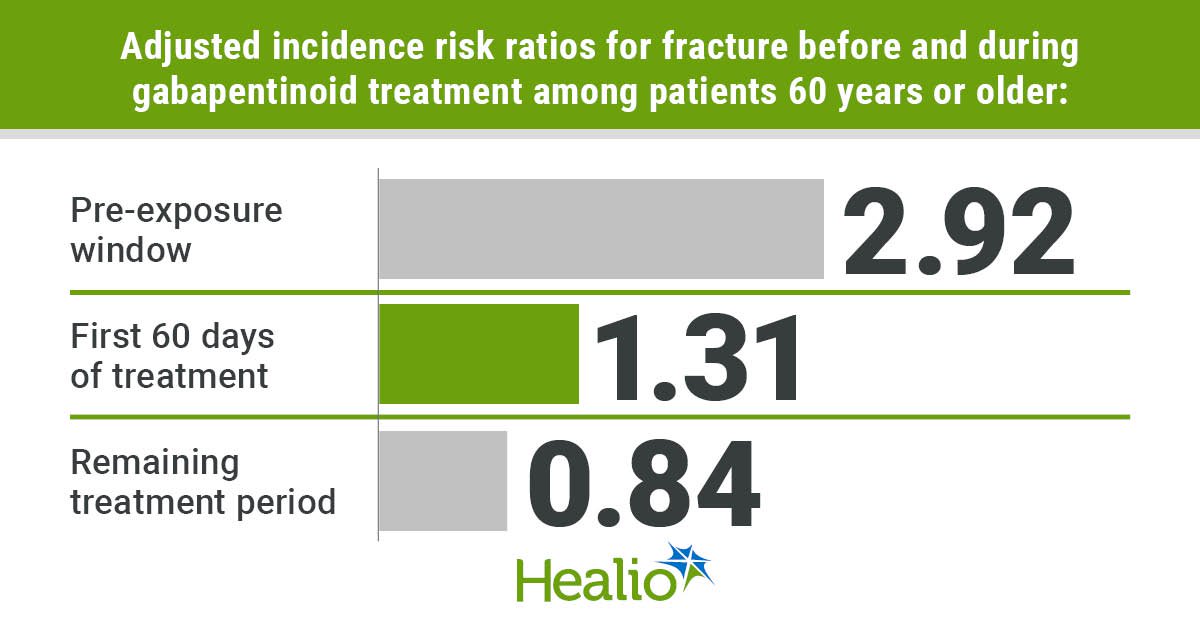
The findings revealed that the incidence rate of fractures was actually highest in the 90 days immediately preceding the initiation of gabapentinoid therapy, rather than during the treatment itself. The researchers noted no sustained elevation in fracture risk during the subsequent, long-term treatment windows.
| Observation Window | Definition / Timeframe | Pooled Fracture Risk Score (vs. Referent) |
| Pre-exposure Window | 90 days prior to initiating gabapentinoid treatment | 2.92 |
| Focal Window 1 | The first 60 days of gabapentinoid treatment | 1.31 |
| Focal Window 2 | The remaining duration of the treatment period | No significant risk increase observed |
| Referent Window | All other periods characterized by non-treatment | Baseline |
Note: Risk scores indicate the relative risk of fracture occurrence compared to the baseline referent window.
Despite the absence of sustained long-term risk, the initial phases of treatment still carry hazards, particularly when central nervous system depressants are coadministered. During Focal Window 1 (the first 60 days of therapy), patients receiving concomitant prescriptions experienced substantially heightened fracture incidence rates:
- Concurrent Opioid Use: Incidence rate ratio of 3.15
- Concurrent Benzodiazepine Use: Incidence rate ratio of 1.91
Conclusions and Clinical Relevance
The authors concluded that the pooled data “do not support a sustained causal relationship between gabapentinoid use and risk for fracture in older adults.” However, Dr. Man cautioned against misinterpreting these results as an absolute endorsement of safety, particularly during the initiation phase or during polypharmacy.
“We are not claiming that gabapentinoids are free from the risks,” Man stated. “Even when [patients] started the treatment on gabapentinoids, it had a 30% higher [fracture] risk compared with nontreatment periods. The more crucial one is when coprescribed with opioids and benzodiazepines…. It looks like the risks go even further.”
To mitigate early therapeutic risks, the investigative team stressed the necessity of robust fall-prevention strategies integrated into the point of prescribing. Dr. Man outlined specific clinical guidance for physicians managing this patient demographic:
“One crucial thing is for clinicians and physicians to assess the fall risks before they start the treatment. The second bit is to start at a lower dose and titrate the medication slowly, because we observed the risk is lower than pre-exposure, but it still attained a relatively higher level…. If the combination [of gabapentinoids and opioids or benzodiazepines] is unavoidable, treat the patient as a high risk for traumatic fracture, and review early.”