Association of GLP-1 Receptor Agonists With Asthma and COPD Exacerbations in Patients With Type 2 Diabetes
Overview
Patients with concurrent type 2 diabetes and airway diseases such as asthma or chronic obstructive pulmonary disease (COPD) may experience fewer respiratory exacerbations when treated with glucagon-like peptide-1 (GLP-1) receptor agonists, particularly semaglutide. According to data presented at the European Respiratory Society International Congress, patients using semaglutide for type 2 diabetes management demonstrated a 38% reduction in asthma exacerbations and a 21% reduction in COPD exacerbations compared with those using sulfonylureas.
Providing context for the study’s rationale, lead researcher Chloe I. Bloom, MBChB, PhD, MSc, clinical associate professor in respiratory epidemiology at the National Heart and Lung Institute, Imperial College London, explained:
“Conditions such as type 2 diabetes and excess weight are very common in people with asthma and COPD and are linked to worse respiratory outcomes.”
Noting that prior evidence pointed toward anti-inflammatory and direct pulmonary benefits of GLP-1 therapies, Dr. Bloom added:
“We wanted to see whether people taking these drugs for diabetes also appeared to have fewer lung flare-ups.”
Study Methodology and Cohorts
The researchers conducted a comparative analysis utilizing the Clinical Practice Research Datalink in the United Kingdom. They compared respiratory outcomes among patients with asthma or COPD who initiated various GLP-1 receptor agonists against a control group of patients who utilized any type of sulfonylurea.
Table 1. Study Population by Initiated Medication Cohort
| Medication Class / Drug | Number of Patients (n) |
| Sulfonylureas (Control) | 20,273 |
| Liraglutide | 2,694 |
| Dulaglutide | 2,303 |
| Semaglutide | 1,493 |
| Exenatide | 1,469 |
| Lixisenatide | 307 |
Outcomes and Reductions in Exacerbations
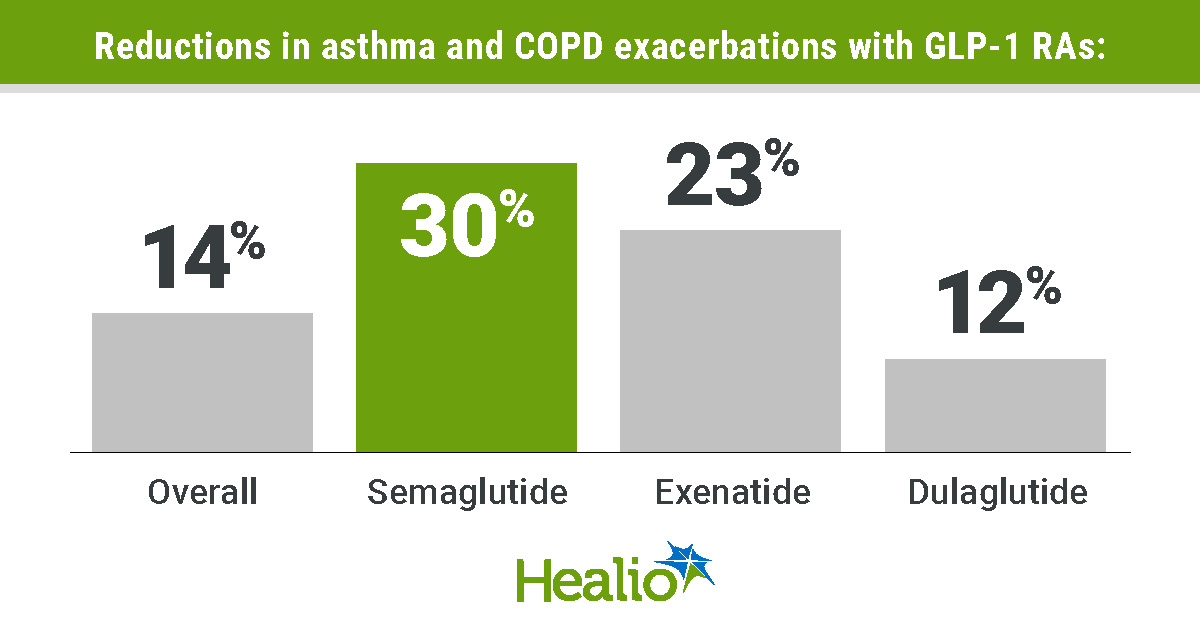
The study found that, as a drug class, GLP-1 receptor agonists were associated with a 14% overall reduction in respiratory exacerbations compared with sulfonylureas. However, efficacy varied significantly depending on the specific GLP-1 agent utilized. Drug dosage did not demonstrate any association with the rate of exacerbations.
“Previous studies have suggested that GLP-1 drugs may reduce respiratory flare-ups, but we wanted to know whether the newer drugs might be more effective than the older ones,” Dr. Bloom stated. “They were, with semaglutide showing the strongest association.”
Table 2. Reduction in Respiratory Exacerbations vs. Sulfonylureas
| Medication | Overall Exacerbation Reduction | Condition-Specific Reduction |
| All GLP-1 RAs | 14% | — |
| Semaglutide | 30% | 38% (Asthma) / 21% (COPD) |
| Exenatide | 23% | — |
| Dulaglutide | 12% | — |
| Liraglutide | No association | — |
| Lixisenatide | No association | — |
Notably, the robust reductions observed with semaglutide were independent of several potential confounding factors. Exacerbation rates were not affected by patient age, smoking status, eosinophil counts, baseline body mass index (BMI), baseline HbA1c, or insulin resistance. Furthermore, the clinical benefits were independent of the degree of weight loss or glycemic control achieved during treatment.
Highlighting this independence from metabolic changes, Dr. Bloom noted:
“The benefit was seen regardless of whether people lost more or less weight or had better or worse glucose control. That suggests the respiratory effects may not simply be a consequence of weight loss or improved diabetes control.”
Clinical Implications and Future Research
While patients presenting with asthma or COPD alongside type 2 diabetes may derive dual benefits from semaglutide, the investigators cautioned against off-label prescribing specifically for airway disease outside of current guidelines.
“Any respiratory benefit may partly reflect weight loss and improved glucose control,” Dr. Bloom remarked. “However, these factors do not appear to explain the whole association, and there may also be more direct beneficial effects in the lungs.”
Emphasizing that these observational findings represent a starting point for further investigation, Dr. Bloom concluded:
“It is too early to change clinical practice on the basis of these findings alone. What they do provide is a strong rationale for clinical trials to test whether GLP-1 drugs can genuinely prevent asthma and COPD flare-ups. We now need to understand why these drugs might help the lungs. Some of the benefit is likely to come from weight loss and improved metabolic health, but those factors do not seem to explain everything. There may also be direct effects within the lungs, and understanding those mechanisms is an important next step.”