46
Association of Nirsevimab Administration With Downstream Reductions in Infant Antibiotic Prescribing
Background and Study Rationale
Immunization with the long-acting monoclonal antibody nirsevimab (Beyfortus) significantly reduces outpatient and inpatient antibiotic prescribing for respiratory tract infections in infants during their first 6 months of life, according to a multicenter cohort study published in Clinical Infectious Diseases.
Although respiratory syncytial virus (RSV) is an exclusively viral pathogen, it frequently precipitates clinical presentations that lead to inappropriate or empirical antimicrobial therapy. Emphasizing the clinical context of the intervention, co-investigators Mahaa M. Ahmed, MS, and Torsten A. Joerger, MD, MSCE, of the Children’s Hospital of Philadelphia (CHOP), noted:
“Nirsevimab is a tool that has shown to be effective in preventing RSV infections in infants since its debut in 2023. Nearly half of children hospitalized with RSV and those who present to outpatient clinics with RSV receive antibiotics. Although antibiotics can be useful in treating bacterial infections, their use can cause various harmful effects.”
To assess whether widespread passive immunization against RSV attenuates downstream antimicrobial exposure, the investigators evaluated antibiotic prescription rates among pediatric primary care patients presenting with acute respiratory tract infections (ARTIs).
Cohort Demographics and Exposure Characteristics
The retrospective evaluation encompassed 15,341 infants receiving primary pediatric care across 32 CHOP network practices during consecutive respiratory virus transmission cycles (2023–2024 and 2024–2025).
The mean (SD) age of the total population was 3.5 (1.7) months, and 48.7% (n = 7,471) were female. Within the study cohort, 48.3% (n = 7,410) received nirsevimab passive immunization during their initial RSV season. Baseline demographic and clinical characteristics were balanced between immunized and nonimmunized cohorts, with the single notable exception that recipients of nirsevimab were comparatively younger at the onset of the respiratory viral season. Patients were observed longitudinally for 6 months following their initial primary care encounter to record all antibiotic prescriptions issued for acute respiratory indications.
Antimicrobial Prescribing Outcomes and Diagnostic Indications
Monoclonal antibody prophylaxis was associated with significant reductions in antibiotic therapy across primary care and inpatient settings:
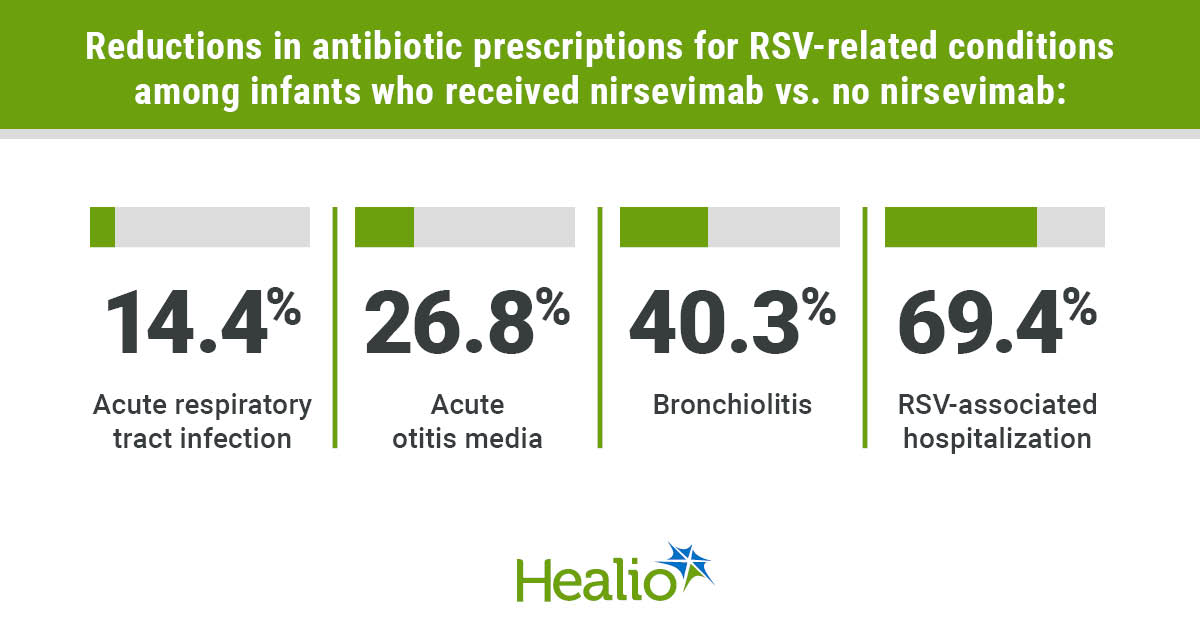
- Outpatient Acute Respiratory Tract Infections: Nirsevimab was associated with a 14.4% relative reduction in overall outpatient ARTI antibiotic prescribing (95% CI, 7.8%–20.6%).
- Bronchiolitis: Outpatient prescriptions for bronchiolitis dropped by 40.3% (95% CI, 25.1%–52.5%).
- RSV Hospitalizations: Antibiotic utilization during RSV-related inpatient hospital stays decreased by 69.4% (95% CI, 4.8%–90.1%).
- Acute Otitis Media (AOM): Antibiotic dispensations for secondary acute otitis media declined by 26.8% (95% CI, 20.8%–32.4%).
- Viral Respiratory Illness: Prescriptions categorized under presumptive viral upper respiratory illnesses decreased by 22.5% (95% CI, 12.6%–31.3%).
Public Health and Stewardship Implications
These findings highlight passive monoclonal antibody immunization as a functional public health mechanism to curb unnecessary pediatric antimicrobial exposure. Commenting on the broader implications for outpatient pediatrics, Ahmed and Dr Joerger stated:
“These findings suggest that nirsevimab, which is used to provide short-term protection against RSV, also has a role in antimicrobial stewardship. The reduction in antibiotic use seen here appears to be driven largely by a decrease in prescribing for both viral infections and acute otitis media.”
They concluded that:
“By preventing upstream viral infections, there can be an indirect downstream reduction in antibiotic prescribing.”
Table 1. Cohort Demographics and Study Baseline Characteristics
| Characteristic / Variable | Cohort Value / Description |
| Total Cohort Size ($N$) | 15,341 infants |
| Sex (Female), % ($n$) | 48.7% (7,471) |
| Age at Baseline, Mean (SD) | 3.5 (1.7) months |
| Intervention Coverage, % ($n$) | 48.3% (7,410) received nirsevimab |
| Clinical Setting | 32 Children’s Hospital of Philadelphia primary care clinics |
| Study Period | 2023–2024 and 2024–2025 respiratory virus seasons |
| Follow-Up Duration | 6 months from first primary care visit |
| Covariate Distribution | Balanced across cohorts; recipients were younger at season onset |
Table 2. Relative Reductions in Antibiotic Prescriptions Following Nirsevimab Immunization by Clinical Indication
| Clinical Diagnostic Category / Encounter Type | Relative Reduction in Prescribing (%) | 95% Confidence Interval |
| RSV-Related Hospitalization | 69.4% | 4.8% to 90.1% |
| Outpatient Bronchiolitis | 40.3% | 25.1% to 52.5% |
| Acute Otitis Media (AOM) | 26.8% | 20.8% to 32.4% |
| Viral Respiratory Infections | 22.5% | 12.6% to 31.3% |
| Total Outpatient ARTIs | 14.4% | 7.8% to 20.6% |
Reference
- Ahmed MM, Joerger TA, et al. Impact of nirsevimab immunization on antibiotic prescribing for acute respiratory tract infections in infants. Clin Infect Dis. Published online September 18, 2026. doi:10.1093/cid/ciag406