49
Association of GLP-1 Receptor Agonists With Psychiatric Outcomes in Bipolar Disorder
Overview
A recent national cohort study conducted in Sweden indicates that glucagon-like peptide-1 receptor agonists (GLP-1 RAs), particularly semaglutide, may significantly lower the risk of psychiatric hospitalization and relapse in patients with bipolar disorder. The study, published in Acta Psychiatrica Scandinavica, investigated this previously unexplored relationship, given the frequent co-occurrence of bipolar disorder, obesity, and diabetes.
According to Mark Taylor, MD, MBBS, BSc (Hons), professor at the school of medicine and dentistry at Griffith University in Australia, the data offer promising dual benefits without evident psychiatric risks.
“Semaglutide may be beneficial in reducing relapse/hospitalization rate. GLP-1s don’t appear to [present] any worrying safety signals (eg, suicidality).”
Study Design and Cohort Characteristics
Taylor and colleagues analyzed registry data spanning from 2009 to 2024 from the National Swedish Registers. The cohort included 14,694 individuals diagnosed with bipolar disorder who were simultaneously prescribed any medication for diabetes. Researchers aimed to determine the impact of GLP-1 RA use on the risk for overall psychiatric hospitalization, as well as specific hospitalizations or work absences related to a bipolar relapse.
Table 1. Cohort Demographics and GLP-1 RA Utilization
| Parameter | Details |
| Total Cohort Size | 14,694 individuals |
| Mean Age | 53.9 years |
| Sex Distribution | 60.5% Female |
| Total GLP-1 RA Users | 5,200 individuals |
| GLP-1 RA Breakdown | – Semaglutide: 70.8% – Liraglutide: 39.4% – Dulaglutide: 15.9% |
| Total Psychiatric Hospitalizations (6-year follow-up) | 5,288 individuals |
Note: Percentages for GLP-1 RA breakdown reflect concurrent or sequential use and may exceed 100%.
Clinical Outcomes
When comparing periods of GLP-1 RA utilization to periods of non-use within the same individuals, the researchers identified significant reductions in the risk of psychiatric hospitalizations.
Semaglutide demonstrated the most robust independent association, while the combined analysis of all three GLP-1 RAs also yielded statistically significant risk reductions. When analyzed independently, liraglutide and dulaglutide did not show a statistically significant reduction in risk, which the authors attributed to limited statistical power due to lower prescription rates.
Table 2. Risk Reductions for Psychiatric Outcomes During GLP-1 RA Use
| Medication / Outcome | Adjusted Hazard Ratio (aHR) | 95% Confidence Interval (CI) | Risk Reduction |
| Semaglutide Use | |||
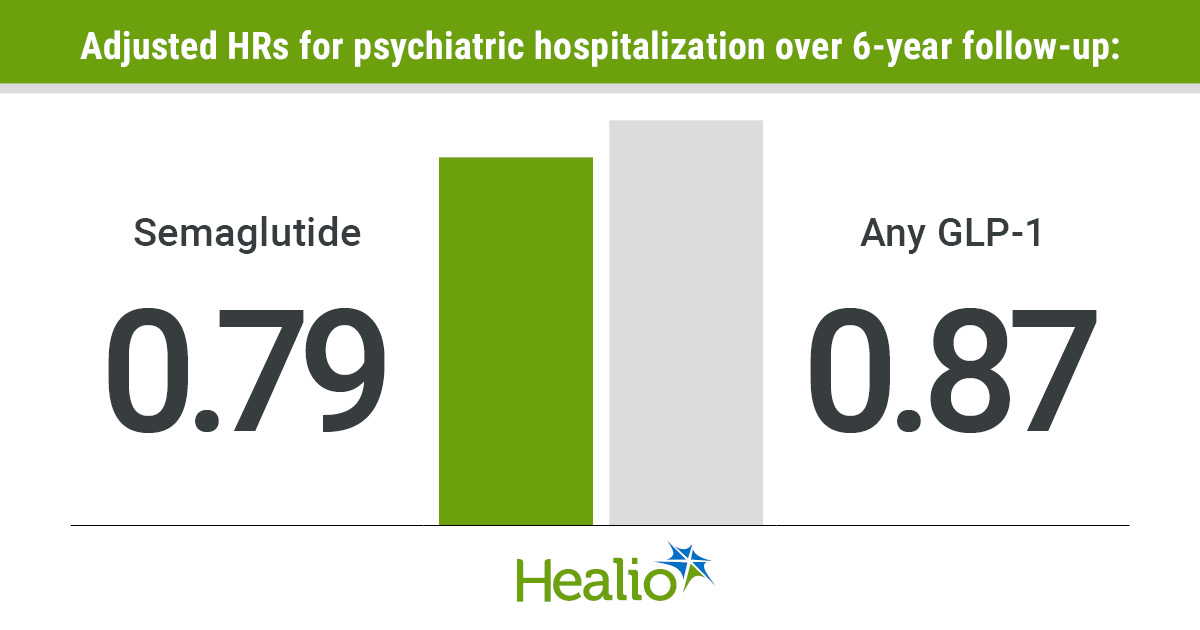
| Any Psychiatric Hospitalization | 0.79 | 0.69–0.91 | 21% |
| Hospitalization for Bipolar Relapse | 0.83 | 0.69–0.99 | 17% |
| Combined GLP-1 RA Use (Semaglutide, Liraglutide, Dulaglutide) | |||
| Any Psychiatric Hospitalization | 0.87 | 0.79–0.97 | 13% |
Addressing the distinct efficacy observed with semaglutide, Dr. Taylor noted:
“Semaglutide was more ‘potent’ than other GLP1s, so perhaps it’s simply more powerful. Our other study also suggests semaglutide can reduce depression and anxiety, which liraglutide does to a lesser extent. We think this is due to a combination of better self-esteem via weight loss and better sugar control, but also direct brain effects, such as reduced inflammation and stress hormone cascades.”
The investigators emphasized the clinical relevance of these findings, noting the historically high rates of hospitalization associated with bipolar disorder:
“The findings on decreased risks for hospitalization during GLP-1 RA use are clinically important as hospitalization rates for bipolar disorder are high, with typical reported 1-year rates of 3% and a lifetime incidence for hospitalization of 75%.”
Expert Perspective and Future Directions
Alberto Augsten, PharmD, MS, provided a clinical perspective on the findings, characterizing them as encouraging given the severe metabolic burdens often exacerbated by mood stabilizers and antipsychotics. However, he emphasized that this data is observational and “remains hypothesis generating.”
“This is an association, not causation, and shouldn’t prompt prescribing semaglutide as a bipolar disorder treatment. The reassuring takeaway is that bipolar disorder alone shouldn’t preclude the use of GLP-1RA when it’s otherwise indicated for obesity or diabetes, with the usual monitoring of mood, adherence and tolerability.”
Dr. Augsten noted several limitations to the study, primarily residual confounding, as patients may be more likely to maintain medication adherence during periods of psychiatric stability. Furthermore, the registry lacked granular data regarding symptom severity, weight loss, and BMI.
Looking forward, clinical trials are investigating agents like brenipatide—a dual GIP/GLP-1 agonist—to determine if incretin-based therapies can directly influence core psychiatric outcomes independently of metabolic improvements. Until such randomized data are available, Dr. Augsten concluded:
“GLP-1RA and related therapies should be viewed as valuable metabolic treatments for appropriately selected patients with bipolar disorder, not as replacements for established mood stabilizing treatment.”